
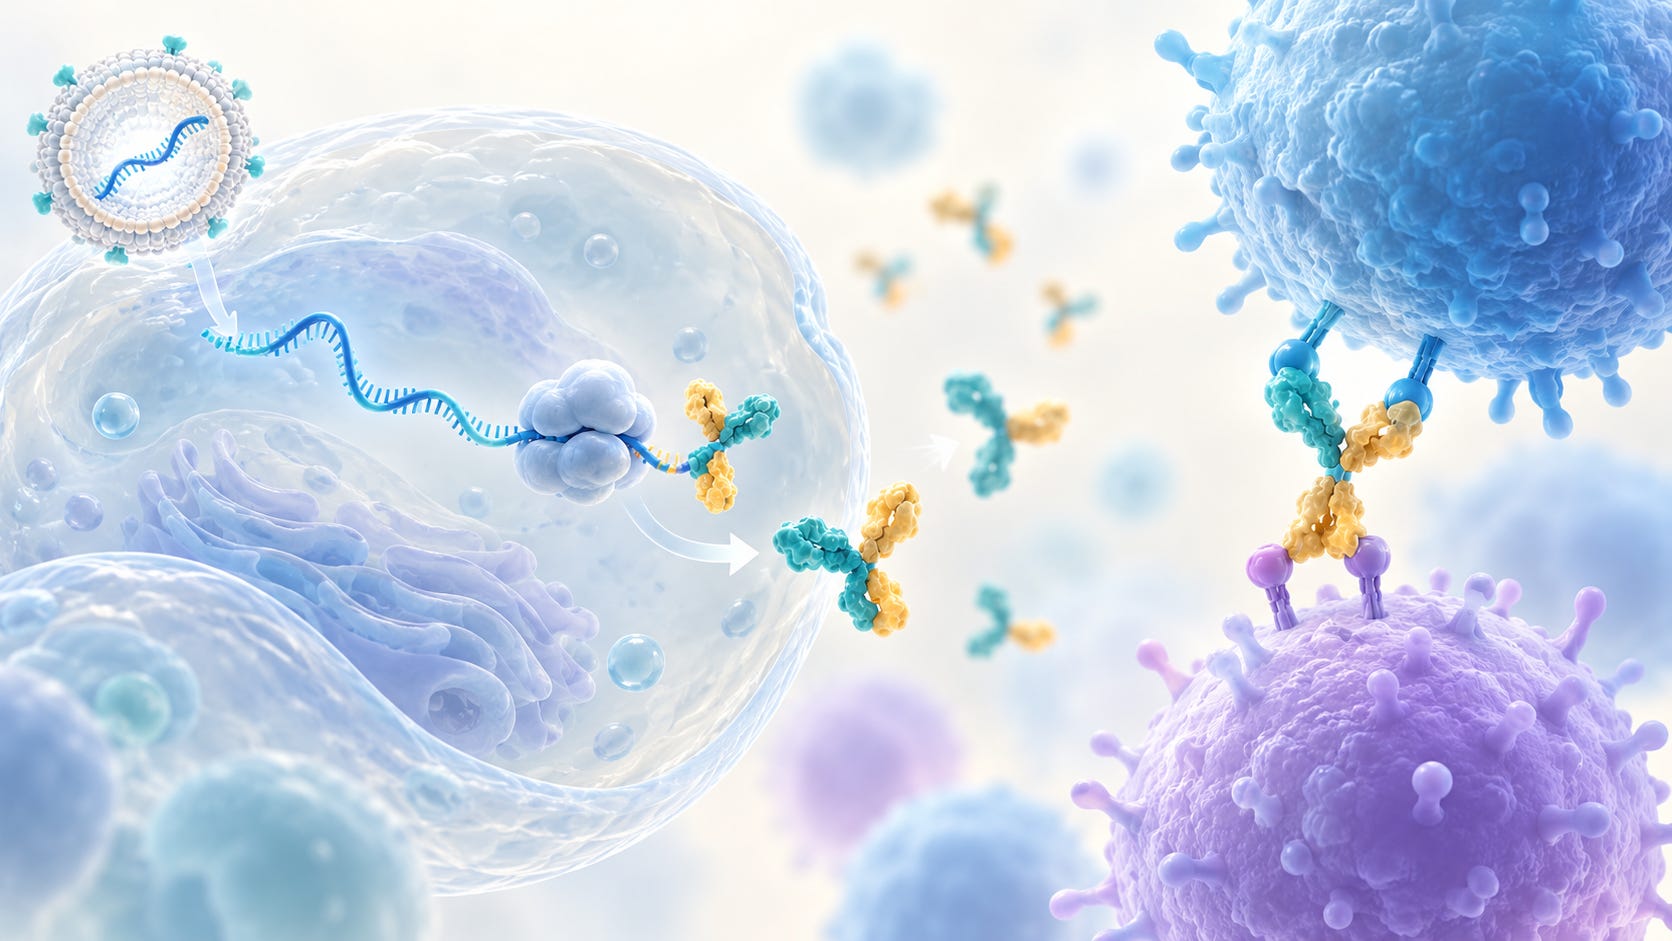
AI-generated conceptual illustration: cells receive mRNA, make and secrete a TCE, and the TCE connects a T cell with a B cell. The cell and protein shapes explain the relationship; they are not measured ABO2203 structures or an established in vivo production site.
A licence for a different way to deliver a protein
On Oct 2, 2026, Abogen announced a licensing and option agreement with Novartis covering exclusive worldwide rights to ABO2203 and options on other RNA programs. ABO2203 is being developed for autoimmune disease. Instead of delivering a finished therapeutic protein, it uses messenger RNA packaged in lipid nanoparticles (LNPs) to direct cells inside the patient to produce a T cell engager (TCE). [S1, S2]
That puts protein production inside the body and adds another step to dose selection. The practical question is how much active protein an mRNA injection produces, how long its effects last, and how the next dose should fit that time course.
Abogen disclosed a $575 million upfront payment and eligibility for up to approximately $7.2 billion in milestones if all options on all programs are exercised and the agreed development, regulatory and commercial milestones are achieved, plus potential sales royalties. The $7.2 billion is a conditional, multi-program ceiling—not the purchase price of ABO2203 alone or revenue already received. The transaction remains subject to closing conditions, including regulatory clearances. [S1]
The RNA carries instructions; the TCE does the work
ABO2203’s T-cell-engaging function is built around CD3 on T cells and CD19 on B cells, bringing the two cell types together so that T cells can eliminate B cells. The later published P4107 design also includes an anti-HSA VHH to extend protein exposure. CD19×CD3 therefore describes the core TCE function, not the entire mature architecture. In autoimmune disease, the intended strategy is B cell depletion followed by an immune reset; durable remission across diseases has not been established. [S1, S4]
Three roles should remain distinct: mRNA supplies the protein instructions, LNPs provide delivery, and the resulting TCE connects the immune cells. ABO2203 does not engineer the patient’s T cells into a CAR-T product.
A recombinant protein medicine is manufactured outside the body before administration. ABO2203 must first deliver mRNA into cells, which then make and secrete the protein. The amount of RNA injected therefore cannot simply be read as the amount of active protein to which the patient is exposed. Here, understanding exposure means following protein concentrations over time and relating that pattern to B cell depletion.
Three autoimmune patients and a separate nine-patient lymphoma study
There are already early human observations in autoimmune disease. The published Cell article reports rapid peripheral B cell depletion, sustained depletion in bone marrow and maintained platelet recovery through six months in three patients with refractory secondary immune thrombocytopenia (ITP). Reported adverse events were grade 1–2, with no cytokine release syndrome (CRS). This moves the discussion beyond extrapolation from cancer studies, but does not establish reproducibility in a larger population. [S4]
The three-patient results above and the technical details in the Extended Read below are drawn from the published Cell article, including its Methods. Those public methods are not a substitute for a regulatory CMC or toxicology dossier.
A separate dose-escalation study enrolled nine patients with relapsed or refractory B cell non-Hodgkin lymphoma, treated with subcutaneous ABO2203. Abogen reported no dose-limiting toxicity (DLT), CRS or immune effector cell-associated neurotoxicity syndrome (ICANS). The earlier American Association for Cancer Research (AACR) abstract also recorded treatment-emergent adverse events in all nine patients, including grade 3–4 events in three; these resolved without sequelae. [S2, S3]
The absence of particular toxicities does not mean the absence of high-grade adverse events. Different diseases, patients and evaluation settings also prevent treating these studies as one 12-patient safety dataset. Neither establishes that ABO2203 is safer than other treatments.
A 5.5-day peak makes the post-injection period matter
The lymphoma study’s AACR abstract reported a median time to peak TCE concentration of 5.5 days after each dose and a mean terminal half-life of 7.9 days. In that dataset, peak protein concentration occurred days after injection, not when the injection was completed. [S3]
The 7.9-day figure is the reported terminal half-life of the protein, not the lifetime of the mRNA. With in vivo protein production, ongoing synthesis and clearance can both shape the observed concentration curve. That single value does not separate their contributions.
For repeat dosing, protein from the previous injection may still be acting when the next injection starts producing more. Protein concentrations, functional activity and B cell recovery therefore matter to interval selection, not just the RNA dose. This is a development question, not a dosing recommendation inferred from those two numbers.
Transient mRNA expression is not an immediate off-switch. Secreted protein may persist, and B cell depletion does not reverse the moment expression stops. The duration of protein production, the duration of its effects and the time required for B cell recovery are related but distinct.
A process change needs more than an RNA-content comparison
Manufacturing still has to establish RNA identity and integrity, control impurities and deliver consistent LNP formulation quality. For a product such as ABO2203, understanding the RNA also means understanding whether its protein can perform the intended function.
The assays answer different questions: expression testing asks whether the intended protein is produced and how much; binding assays test target recognition; cell-based functional assays test whether the protein can direct T cells to eliminate target B cells. One readout does not answer all three.
These readouts can be interpreted alongside clinical PK/PD, but their roles in lot release, characterization or comparability depend on the product and development stage. The full clinical mechanism does not need to become one release assay.
Consider a hypothetical process change, not a reported ABO2203 manufacturing result: RNA content remains similar and an expression assay shows little change. The first question is whether analytical and functional evidence is sufficient to support comparability. If material uncertainty remains, nonclinical or clinical bridging can be added according to the change, development stage and residual risk. The point is not to force every process change into human PK; it is to match the evidence package to the remaining uncertainty. [S10]
The next evidence is about repetition
ABO2203 provides an early human example of mRNA-directed therapeutic TCE production, including observations in autoimmune disease. That is a meaningful development beyond the transaction headline.
The next tests are whether the findings reproduce in larger studies, how successive doses interact, how deeply B cells are depleted and how long recovery takes, and whether product or process changes preserve consistent function. The deal sets out commercial scope and potential future payments. It does not substitute for clinical and product evidence.
Sources
S1 · Abogen official agreement announcement
S2 · Abogen official AACR clinical report
S3 · AACR CT032 — original clinical abstract
S4 · Wang et al., Cell — refractory secondary ITP and ABO2203 development
S10 · FDA / ICH Q5E — manufacturing-process comparability principles
Extended Read — How ABO2203 Was Built: From mRNA Design to Human Dosing—and the Novartis Deal
The Novartis agreement is the latest visible milestone in the ABO2203 story, not the beginning. The public record stretches back through an earlier blinatumomab-encoding program, protein engineering, mRNA cassette screening, LNP screening, animal pharmacology, route selection and dose escalation in humans. Read in sequence, those disclosures show something more useful than a list of technical features: they show how one design decision created the next development question. [S5–S9]
Before ABO2203, there was ABO2015
At AACR 2024, Abogen described ABO2015 as an mRNA–LNP encoding the amino-acid sequence of blinatumomab, a CD19×CD3 T-cell engager whose short protein half-life ordinarily requires prolonged infusion. ABO2015 moved the production step in vivo: LNP-delivered mRNA instructed cells to make the TCE. The poster also reported an investigator-initiated intravenous study in relapsed or refractory B-cell acute lymphoblastic leukemia. That brought the modality into humans; the claim of flatter, longer exposure versus direct protein dosing remained supported mainly by the poster’s preclinical comparisons. [S5]
ABO2203 was presented as the next step. Abogen had changed both the encoded TCE and the mRNA expression system. In non-human primates, the 2024 poster reported that a single 0.01 mg/kg intravenous dose produced a TCE half-life of 18.8 days, a Tmax of 1.5 days and a Cmax of 202 ng/mL. Those are company-reported preclinical data, not a human head-to-head comparison, but they explain the original engineering objective: make the protein last longer and make the mRNA produce it more effectively. [S5]
Design the protein before optimizing the RNA
The later patent record shows that Abogen did not begin with one fixed TCE sequence. It compared multiple CD19/CD3 constructs and selected a lead designated ABO-CD19/CD3-1 after examining tumor-cell killing, cytokine release and pharmacokinetics in preclinical systems. The lead architecture adds a human-serum-albumin-binding VHH to the CD19- and CD3-binding domains. Albumin binding is a familiar way to extend the circulation time of small proteins. [S7]
The Cell article describes the mature ABO2203-encoded protein, P4107, as incorporating an attenuated CD3-binding domain and an anti-human-serum-albumin domain for half-life extension. That combination matters. The mRNA platform can spread protein production over time, but the protein itself was also engineered to change how strongly it activates T cells and how long it remains in circulation. ABO2203’s pharmacology is therefore the product of both layers, not an LNP effect alone. [S8]
The patent nomenclature is useful design history, not a clinical batch record. It should not be read as proof that every patented sequence or construct entered the final clinical product.
The mRNA was screened as a cassette, not merely as a CDS
The patent describes the mRNA as a complete expression cassette: 5′ cap → 5′UTR → signal peptide → TCE coding sequence → 3′UTR → poly(A). It lists several candidate 5′UTRs, including SEQ ID 77, 78, 162 and 163; candidate 3′UTRs including SEQ ID 79, 80 and 164; signal-peptide sequences; multiple codon-optimized coding sequences; and a poly(A) embodiment of about 105 nucleotides, SEQ ID 85. It also allows N1-methylpseudouridine and a 5′ cap. [S7]
The most informative experiment is simpler than the sequence list. Four mRNAs—mRNA-1 through mRNA-4—encoded the same lead protein, yet mRNA-2 produced the highest protein yield in vitro. Abogen then formulated mRNA-1 and mRNA-2 into LNPs; mRNA-2-LNP gave the best expression in mice. In other words, the screen held the protein target constant while changing the RNA implementation. The backbone around the CDS mattered enough to change the winner. [S7]
The public patent does not give us a clean clinical specification sheet mapping “mRNA-2” to one exact final combination of 5′UTR, signal peptide, CDS variant, 3′UTR and poly(A) sequence. We can identify the design space and the winning candidate label, but we should not pretend that every listed embodiment is part of the clinical construct.
What the public IVT record shows—and what it does not
The patent examples describe a research-scale process built around a T7 template, T7 in-vitro transcription, DNase digestion, LiCl precipitation, post-transcriptional enzymatic capping and additional purification. Cap1 was generated with vaccinia capping enzyme plus mRNA 2′-O-methyltransferase rather than a co-transcriptional cap analog. Patent examples also describe chromatographic purification. [S6, S7]
The Cell methods disclose a later, more clinical-facing process: ABO2203 mRNA was transcribed from linearized template ABO2203-LP with T7 RNA polymerase and N1-methylpseudouridine-containing nucleotides, followed by DNase digestion, POROS Oligo(dT)25 purification, heat/cool treatment, post-transcriptional Cap1 enzymatic capping and a second Oligo(dT)25 step. The listed core enzymes carry GMP-designated catalog numbers, but those catalog designations do not establish clinical-lot genealogy or a complete GMP process. [S8]
Compared with the earlier LiCl/HPLC patent examples, the public methods clearly differ. What remains unknown is when and why those operations changed and how research, toxicology and clinical lots were bridged.
One more detail matters for process interpretation. The patent places the linearization site downstream of an encoded poly(A) sequence, consistent with template-encoded poly(A) in those examples. The Cell paper does not separately state the clinical poly(A) length, so the approximately 105-nt patent embodiment should not be promoted to a confirmed clinical specification.
LNP screening continued; the Cell formulation uses Lipid 3201
The discovery work did not begin with a single ionizable lipid either. The patent describes mRNA-2 formulated with several candidate lipids, including lipid 5, compound 03-135 and compound 01-1, and reports similar mouse expression pharmacokinetics among those examples. [S7]
The Cell paper identifies the later ABO2203 formulation more specifically. Its key-resources table names the ionizable lipid as Lipid 3201, CAS 2803435-09-6, together with DSPC, cholesterol and DMG-PEG2000. The methods give a broad component range and a standardized example of 50/10/38.5/1.5 mol% for ionizable lipid/DSPC/cholesterol/PEG-lipid. Total lipid:mRNA is described at approximately 10:1–30:1 by weight. The ethanolic lipid phase is mixed with aqueous mRNA at 1:3 by volume in a microfluidic apparatus, followed by dialysis into DPBS and 0.2-μm sterile filtration. Particle size and distribution, RNA concentration and encapsulation are among the disclosed tests. [S8]
That is enough to say that the later ABO2203 formulation described in the Cell paper uses Lipid 3201; it is not enough to reconstruct the lipid’s chemistry from a name. We have a CAS identifier, but the public materials reviewed here do not give a reliable systematic structure name that can be tied to the clinical product without further patent mapping.
Preclinical data changed the route of administration
A particularly clean development decision appears in the route work. The 2024 poster showed ABO2203 intravenously in non-human primates. The later Cell study compared intravenous and subcutaneous ABO2203 at 3 μg/kg in cynomolgus monkeys. Subcutaneous delivery produced a slower-rising profile with a longer Tmax and, in that small experiment, higher Cmax and AUC. The authors explicitly state that the slower rise, the possibility of sustained target engagement and administration convenience led them to select the subcutaneous route for clinical development. [S5, S8]
This is the kind of transition that makes the development history useful. The formulation did not merely “work in animals.” The animal PK answered a concrete question—how to deliver the same encoded protein—and changed the route taken into humans.
The Cell paper also reports repeat subcutaneous dosing in hCD3/hCD19 transgenic mice: once weekly for five doses at 50 or 300 μg/kg, followed by histopathology of heart, liver, spleen, lung, kidney and axillary lymph nodes. The paper reports no treatment-related histopathological changes in heart, liver, lung or kidney, with dose-related reduction in splenic lymphoid cellularity consistent with the pharmacology. [S8]
What the public record says about IND-enabling toxicology—and what it does not
This is where the public story has a real gap. EULAR states that safety was confirmed in rodents and non-human primates. The Cell paper says “preliminary toxicology” supported an adequate safety window when the first-in-human starting dose was chosen. The repeat-dose mouse histopathology described above also adds useful safety information. [S8, S9]
None of the public sources reviewed here, however, identifies a formal pivotal GLP toxicology study by study number, GLP status, species and group size, dose schedule, toxicokinetics, recovery period, NOAEL or HNSTD. Nor do they disclose the genealogy of the toxicology lot versus the clinical GMP lot or a formal tox-to-clinical comparability package.
That absence should not be read as evidence that such work was not done. It means only that the public record does not support writing the usual IND-enabling package as if we had seen it. For a development dossier, this is one of the most important remaining unknowns.
Human dosing became a PK/PD feedback problem
The autoimmune first-in-human study, NCT06747156, makes the logic unusually visible. The Cell methods say the trial’s starting dose was selected from allometric human PK prediction, a preclinical ABO2203 EC50 range of 25–150 pg/mL, a conservative target peak concentration of 150 pg/mL and reference to blinatumomab exposure. A 1-μg subcutaneous dose was predicted to approach but not exceed that target, while preliminary toxicology supported the safety window. Subsequent step-up and treatment doses were guided by real-time PK, pharmacodynamic and safety assessments. [S8]
The three ITP patients reported in Cell were treated later in that escalation path: 120 μg on Day 1 followed by 480 μg weekly. Two patients did not receive the final planned dose because complete platelet response and profound B-cell depletion had already been observed. That is a direct example of human pharmacology feeding back into the regimen rather than a fixed RNA dose being treated as the whole product. [S8]
Human PK makes the separation visible. After 120 μg, mean P4107 Cmax was 2.8 ng/mL; after the first 480-μg dose it was 50.5 ng/mL and increased further with repeat dosing. Mean P4107 Tmax was about five days and effective half-life about eight days. The measured Lipid 3201 component peaked at about three days and had a terminal half-life of about two days. These are different exposure clocks; lipid-component PK should not be read as the lifetime of an intact LNP particle. [S8]
A separate EULAR 2026 disclosure described 15 refractory autoimmune-disease patients across intra-patient escalation, fixed-dose escalation and expansion, with weekly subcutaneous dosing for one month and no premedication. That dataset is a different disclosure window from the three-patient Cell report and should not be numerically pooled with it. [S9]
Oncology asks a different question of the same platform
ABO2203 also entered a separate first-in-human B-cell non-Hodgkin lymphoma study (NCT07072169), with weekly subcutaneous escalation up to 1,920 μg. In nine treated patients, all had treatment-emergent adverse events and three had grade 3–4 events. The abstract reported median TCE Tmax of 5.5 days, mean terminal half-life of 7.9 days and mean LNP-component half-life of 2.4 days. [S3]
Those oncology data are not a safety denominator for the autoimmune program. Here they serve mainly as an independent exposure check: delayed, multi-day TCE exposure also appeared in another population and dose-escalation program.
By the clinical stage, process questions become product questions
ABO2203 cannot be reduced to “the sequence.” Protein architecture affects activity and persistence; the RNA cassette affects expression; IVT, capping and purification define the RNA entering formulation; LNP and route shape delivery and exposure; and human PK/PD ultimately informs the regimen.
That complexity matters after a process change. A research disclosure using LiCl precipitation and screened ionizable lipids is not automatically equivalent to later material described with Oligo(dT) purification and Lipid 3201. The first bridge is analytical and functional: RNA quality, delivery-relevant attributes, expression, binding and cell function. If those data leave material uncertainty, nonclinical or clinical bridging can be added in proportion to the change and residual risk; ICH Q5E does not prescribe a routine clinical comparability step. [S10]
The public record still does not disclose the full commercial-scale process, complete release specifications, stability program or formal tox-to-clinical lot comparability. Those gaps limit how far the discovery process can be called a transferable platform.
Why the Novartis agreement belongs at the end of the story
Seen against that development history, the October 2026 agreement is more informative than the headline number alone. The proposed agreement covers exclusive worldwide rights to ABO2203 and gives Novartis options on additional programs using Abogen’s RNA platform. Abogen disclosed a $575 million upfront payment and potential milestones of up to approximately $7.2 billion across programs if all options are exercised and the relevant milestones are achieved, plus royalties. The transaction remains subject to closing conditions. [S1]
The deal does not prove that ABO2203 is clinically superior, that the manufacturing process is commercially mature or that Lipid 3201 is a broadly validated delivery platform. The agreement structure does, however, show commercial interest beyond a single asset: Novartis negotiated rights to ABO2203 plus options on additional RNA-platform programs. That is evidence of platform optionality in the transaction, not scientific validation of every element of the platform.
For RapidGene, the most useful lesson is the path, not the price tag. The public record shows a sequence of development decisions: protein design defined the lead TCE; cassette screening narrowed the RNA implementation; LNP and animal PK work informed delivery; the IV-versus-SC experiment changed the clinical route; and human PK, pharmacodynamics and safety were used to guide dose escalation and interval. The remaining questions are equally concrete: the exact final cassette definition, the public chemical mapping and control strategy around Lipid 3201, the formal GLP toxicology package, tox-to-clinical lot comparability, and the scale, stability program and specifications that will have to survive later-stage development.
Extended Read sources
S6 · WO2024131874A1 — early mRNA-encoded CD19/CD3 TCE patent
S7 · WO2025214418A1 / PCT/CN2025/088099 — optimized TCE, mRNA and LNP development
S8 · Wang et al., Cell — ABO2203 design, manufacture, preclinical and first-in-human ITP study
S9 · EULAR 2026 POS0378 — broader autoimmune preclinical-to-clinical translation
S10 · FDA / ICH Q5E — manufacturing-process comparability principles